


Organoid-Based Antibody-Drug Conjugate Evaluation Platform
Key Challenges in Current ADC Development and Preclinical Evaluation
Critical problems that occur during ADC development
- On-target toxicity in normal tissues: Antibody binds to target on both cancer and healthy cells, causing damage.
- Payload-driven systemic toxicity: Toxic drug (payload) leaks and affects the whole body.
- Differential target expression: Target protein is expressed differently between tumors and normal tissues.
- Bystander effect: Released drug kills neighboring cells (can be useful or harmful).
Limitation of Cell Line-based Models (2D)
- Flat 2D culture does not mimic real tissue structure.
- Lacks proper microenvironment (no blood vessels, immune cells, or matrix).
- Target expression differs from real human tissues.
- Poor at reproducing ADC internalization and drug release.
Limitations of Animal Models
- Species differences in antigen expression and drug metabolism.
- Poor cross-reactivity with human-specific antibodies.
- Difficult to predict human organ-specific toxicity.
SOLUTION:
Human Organoid-based Systems (3D)
- Human-relevant antigen expression across tissues
- Tumor vs normal organoid comparison for safety margin
- Captures intra- and inter-patient heterogeneity
- ️ Enables integrated efficacy and toxicity assessment
- Expression level–dependent efficacy evaluation
- Improved prediction of human pharmacology and toxicity
Ready to start your project?
Comprehensive Organoid-Based Workflow for ADC Evaluation
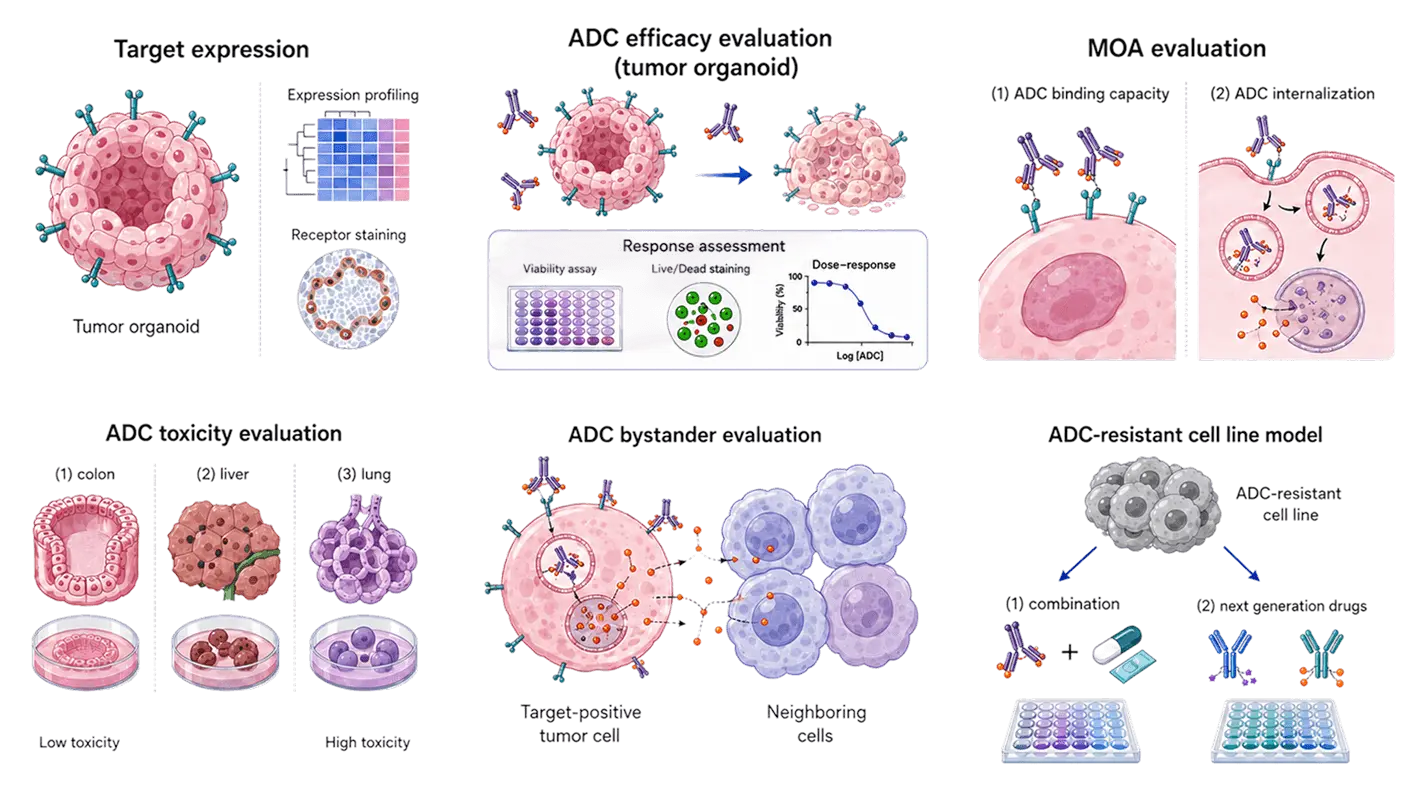
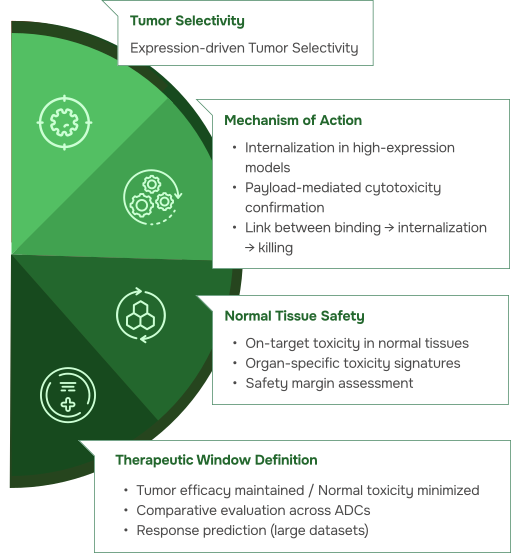
Lambda Biologics’ organoid-based ADC evaluation workflow supports multiple stages of preclinical ADC development, from target expression profiling and tumor efficacy assessment to MOA analysis, toxicity evaluation, bystander effect testing, and ADC-resistance model development. By integrating patient-relevant tumor and normal organoid models, this platform helps generate more predictive insights into ADC efficacy, safety, and therapeutic potential.
Why Lambda Biologics?
Organoid-Centered ADC Expertise
ADC-Specific End-to-End Workflow
Human-Relevant, NAM-Aligned Deliverables
Strengthen preclinical decision-making with structured 3D human-model data designed to complement conventional studies and support the industry’s shift toward New Approach Methodologies.
Decision-Ready Scientific Partnership
Customized efficacy testing platforms
-
#1CANCER ORGANOID ONLY
-
#2CO-CULTURE OF CANCER ORGANOID & T-CELL
-
#3CO-CULTURE OF CANCER ORGANOID & CAF
-
#4CO-CULTURE OF CANCER ORGANOID & NK CELLS
-
#5THE INFILTRATION ASSAY OF MDSC CELLS
-
#6SPATIAL BIOLOGY (IMMUNE PROFILING)
Frequently Asked Questions
What are Antibody Drug Conjugates (ADCs)?
Antibody-drug conjugates, or ADCs, are targeted cancer therapies that combine a monoclonal antibody, a chemical linker, and a cytotoxic payload. The antibody binds to a tumor-associated antigen and helps deliver the payload more selectively to cancer cells. ADC performance depends on factors such as target expression, internalization, linker stability, payload release, tumor heterogeneity, bystander effect, resistance, and normal tissue toxicity, making human-relevant preclinical models important for ADC evaluation. The FDA’s ADC clinical pharmacology guidance also frames ADC development around cytotoxic small-molecule payloads and related bioanalytical, exposure-response, dosing, and safety considerations.
As of June 2026, the FDA-approved ADC landscape continues to expand across solid tumors and hematologic malignancies. Recent FDA activity includes Datroway / datopotamab deruxtecan-dlnk for HR-positive/HER2-negative breast cancer, EGFR-mutated NSCLC, and triple-negative breast cancer; Emrelis / telisotuzumab vedotin-tllv for c-Met–high non-squamous NSCLC; Blenrep / belantamab mafodotin-blmf for relapsed or refractory multiple myeloma; and Decnupaz / pivekimab sunirine-pvzy for BPDCN.
How is ADC target expression pre-screened before efficacy testing?
ADC target expression can be assessed before efficacy testing using transcriptomic, protein-level, and spatial profiling methods. Common approaches include RNA-seq, FACS/flow cytometry, immunostaining, and spatial profiling to help identify suitable PDO, PDO-CAF, PDOX-CAF, tumor organoid, and normal organoid models for antibody-drug conjugate evaluation.
Target expression pre-screening is especially important for ADC studies because antigen abundance, expression heterogeneity, and tumor-versus-normal selectivity can strongly influence ADC response. By selecting models with target-high, target-low, and heterogeneous expression patterns, researchers can better evaluate whether ADC activity correlates with antigen level and identify the most informative models for efficacy, toxicity, and resistance studies.
At Lambda Biologics, target expression assessment can be integrated with organoid model selection to support more rational ADC study design and reduce the risk of uninformative preclinical testing.
What methods are used to evaluate the ADC bystander effect in co-culture organoid models?
The ADC bystander effect can be evaluated using tumor–stromal co-culture organoid systems, such as tumor organoid–CAF models. In these models, tumor cells and cancer-associated fibroblasts can be separately labeled or detected using cell-specific fluorescent markers, lineage markers, imaging-based segmentation, or flow-based readouts.
This enables individual quantification of tumor-cell killing and CAF apoptosis, helping distinguish direct target-mediated ADC cytotoxicity from bystander payload effects. Relevant endpoints may include cell viability, apoptosis markers, caspase activation, DNA damage response, and spatial distribution of affected cells within the co-culture system.
How are ADC efficacy and normal tissue toxicity assessed side by side?
ADC efficacy and normal tissue toxicity can be assessed side by side by comparing drug response in tumor organoids and relevant normal organoid models. Tumor organoids are used to evaluate anti-tumor activity, while normal organoids help assess tumor selectivity, on-target/off-tumor effects, payload-related toxicity, and therapeutic window.
Depending on the ADC target and payload class, normal organoid models may be selected from tissues with expected clinical relevance, such as colon, liver, lung, skin, or other epithelial tissues. Endpoints can include viability, apoptosis, morphology, tissue-specific damage markers, antigen expression, and dose-response sensitivity.
This tumor-versus-normal comparison helps determine whether an ADC shows preferential activity against cancer models while maintaining reduced toxicity in normal human-relevant systems. Lambda Biologics applies this organoid-based approach to support ADC candidate prioritization and translational risk assessment.
When are extended culture protocols recommended for TOP1 inhibitor-class ADCs?
Extended culture protocols are recommended when ADCs carry payloads with delayed pharmacodynamic effects, such as topoisomerase I inhibitor-class payloads, also known as TOP1i payloads. A standard short-term assay window, such as 3–5 days, may not fully capture delayed DNA damage response, cell-cycle arrest, apoptosis induction, or time-dependent cytotoxicity.
For TOP1i-class ADCs, assay duration can be adjusted based on organoid growth kinetics, model stability, dosing schedule, payload mechanism of action, and endpoint requirements. Extended protocols may support more accurate assessment of delayed tumor killing, residual viable cell populations, post-treatment regrowth, and early resistance-associated phenotypes.
What study design is recommended for dual-payload ADC evaluation using organoid models?
Dual-payload ADCs can be evaluated using comparative organoid studies that include single-payload ADCs, unconjugated antibody controls, free payload controls, isotype ADC controls, and standard treatment references. For colorectal cancer and other solid tumor studies, the model panel should ideally include target-high, target-low, and heterogeneous-expression organoids to assess whether the dual-payload design provides broader or stronger activity across biologically diverse tumors.
Key readouts may include dose-response curves, IC50/EC50, maximum killing effect, apoptosis, DNA damage response, target expression–response correlation, and post-treatment residual cell analysis. These studies can support ADC candidate ranking, mechanism-of-action analysis, resistance exploration, and translational decision-making. However, organoid data should be positioned as a human-relevant preclinical indicator, not as a standalone predictor of clinical superiority.
